Experience and observation
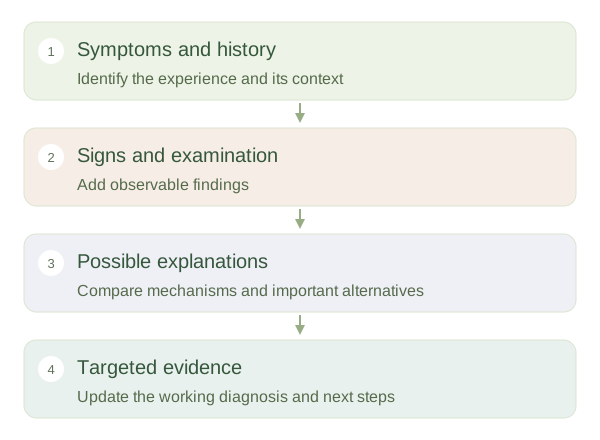
A is something a person experiences and reports, such as nausea, breathlessness or pain. A is a finding that can be observed or measured, such as a rash, a recorded fever or a laboratory abnormality. The same underlying process can create both: someone may feel hot, while a thermometer records a raised temperature. Neither category is automatically more important. Symptoms provide access to the person’s experience, while signs add observable information. Both can be influenced by timing, context and how carefully they are assessed.
Building a clinical explanation
 Open diagram larger ↗
From clues to possible explanations
A diagnosis identifies a condition or process that explains the available evidence. Clinicians usually begin with several possibilities, called a . They consider pattern, onset, medical history, examination findings and risk factors. A test is useful when it helps answer a specific question, rather than simply producing more data. Similar symptoms can arise from different mechanisms, and one disease can present differently in different people. The aim is to find the explanation that best fits while remaining alert to important alternatives and missing information.
Reasoning stays open to revision
Clinical reasoning involves updating an assessment as new evidence appears. A may change after observation, a test result or an unexpected course. This is not necessarily a failure: uncertainty is part of interpreting incomplete information. However, prematurely fixing on the first explanation can cause later clues to be overlooked. Some decisions concern urgency before a precise diagnosis is known, because dangerous possibilities need prompt assessment. Learning anatomy and physiology helps you understand why a might occur, but it does not make one symptom a reliable diagnostic shortcut. The useful habit is to connect evidence, mechanism and uncertainty rather than match a word to a disease label.