Injury starts a coordinated response
Tissues can be injured by mechanical damage, interrupted blood supply, infection, chemicals or other stresses. Cells may recover if the disturbance is limited, but more severe injury can cause cell death. Damaged tissue releases signals that recruit inflammatory cells and begin clearing debris. Inflammation can help remove a harmful cause and organise repair, although prolonged or excessive inflammation can add damage. The response depends on the tissue, the severity and whether its supporting architecture remains intact. Healing is therefore a coordinated process rather than a single event.
Two outcomes of repair
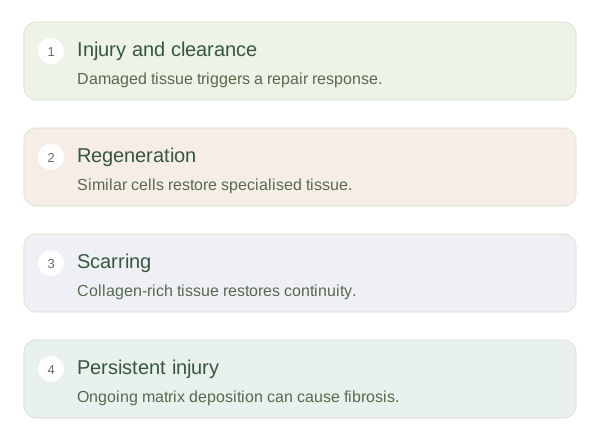 Open diagram larger ↗
Replacing cells or filling a gap
restores damaged tissue using cells similar to those lost. Its extent depends partly on whether surviving cells or stem-cell populations can divide and rebuild the structure. Repair by scarring instead fills a defect with connective tissue rich in collagen. Fibroblasts, new small vessels and inflammatory cells contribute to an early repair tissue before the matrix is remodelled. These processes often occur together. A can make a wound mechanically continuous without recreating specialised structures such as hair follicles, normal heart muscle or the fine architecture of an air sac.
When repair becomes a burden
means excessive or persistent accumulation of connective-tissue matrix. Repeated injury can keep repair signals active, gradually replacing functional tissue or stiffening an organ. Fibrotic lungs may expand less easily; extensive liver scarring can disrupt blood flow and normal organisation. The problem is not that collagen is inherently harmful: it is essential for strength, but its amount and arrangement must suit the task. Remodelling continues after a wound appears closed, and strength changes over time. Understanding healing means asking both whether the gap has closed and whether the original tissue’s function has been restored.