Persistent limitation of airflow
Chronic obstructive pulmonary disease, or , is a group of conditions characterised by persistent airflow obstruction in an appropriate clinical setting. It commonly involves small-airway disease and in varying proportions. Long-term exposure to tobacco smoke is an important cause, but other inhaled exposures and genetic factors can contribute. COPD is not simply a normal result of ageing or another name for every chronic cough. Symptoms, exposure history and lung-function testing help establish the diagnosis and distinguish other causes of breathlessness.
Why expiration becomes difficult
 Open diagram larger ↗
What changes inside the lungs
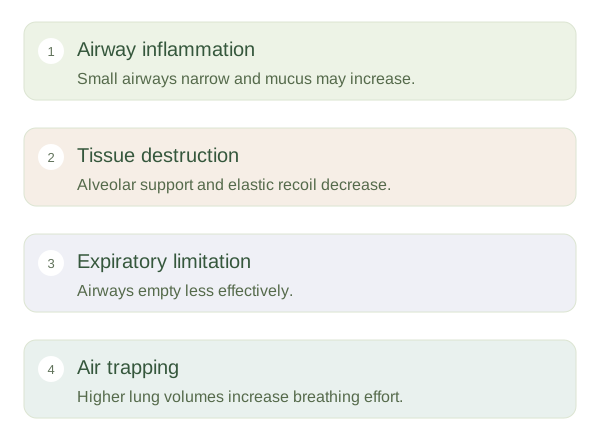
Small airways can become inflamed, narrowed and affected by excess mucus. In , alveolar walls and their supporting tissue are damaged, reducing gas-exchange surface and elastic recoil. Normal lung recoil helps drive air out and holds small airways open through surrounding tissue attachments. With reduced support, those airways can narrow during expiration, trapping air. The person may breathe at a higher lung volume and work harder to move additional air. The difficulty is therefore not only getting oxygen in; effectively emptying and mechanically using the lungs also matters.
The consequences vary
Reduced gas exchange and ventilation–perfusion mismatch can impair blood oxygenation, while some people also retain carbon dioxide. Exercise becomes demanding because breathing uses more effort and available ventilatory reserve is limited. Exacerbations are episodes of worsening symptoms, often related to infection or environmental triggers, and can have serious consequences. can coexist with asthma or cardiovascular disease, so the mechanism of breathlessness may be mixed. Not all damaged tissue can be restored, but several approaches can improve symptoms and reduce risk. The foundational concept is a combination of narrowed pathways, lost structural recoil and uneven gas exchange rather than one simple obstruction.