Infection at the exchange surface
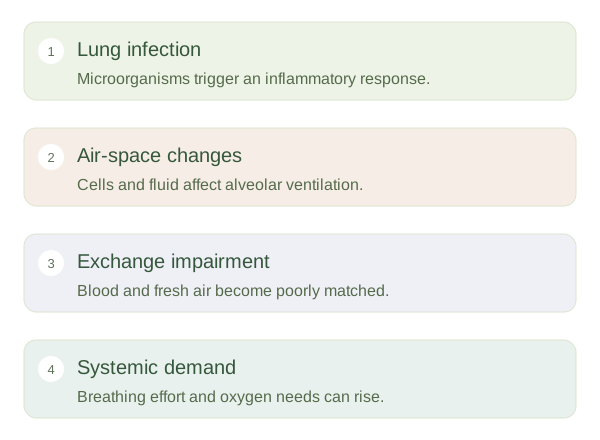
is an infection involving lung tissue, commonly including alveoli. Bacteria, viruses and fungi can cause it, with the likely organism depending on circumstances. Normally, alveoli contain air beside a thin barrier separating it from capillary blood. During pneumonia, inflammatory cells and fluid can enter affected air spaces. This changes the normal interface and makes parts of the lung less effective at exchanging gases. Pneumonia is therefore different from an infection limited mainly to the large conducting airways, although symptoms can overlap.
Pneumonia and gas exchange
 Open diagram larger ↗
Why breathing and oxygenation change
An affected region may receive blood but too little fresh air because its alveoli contain inflammatory material or are poorly expanded. This can lower oxygenation. The lung can also become less compliant, requiring greater effort to expand. Fever and inflammation increase metabolic demands while the lungs may be less able to meet them. Cough helps move secretions but does not identify the precise organism. Chest discomfort can occur when nearby pleural surfaces are irritated. The extent and distribution of affected tissue influence the physiological burden.
Severity is a whole-person question
Some infections remain relatively local, while others involve larger areas or provoke complications. Fluid can accumulate around the lung, and a severe systemic response can lead to sepsis. Age, immune function and existing heart or lung disease affect reserve. Clinicians use history, examination and selected tests, sometimes including imaging or microbiology, rather than identifying from one symptom alone. An image may show increased opacity, but technique and other diseases can produce similar appearances. The central learning point is that filling or disrupting the gas-exchange region changes both air delivery and the diffusion environment, linking a local infection to wider oxygen and circulatory consequences.