More than a low urine volume
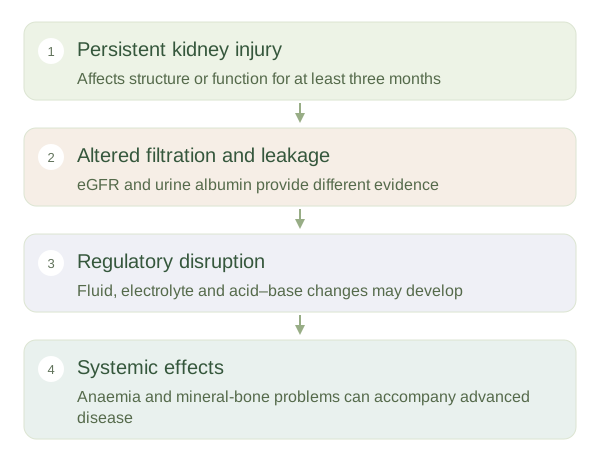
Chronic kidney disease, or CKD, means abnormalities of kidney structure or function persist for at least three months and have health implications. It may involve reduced filtration, evidence of kidney damage or both. A person can still produce substantial urine while having impaired kidney function. The kidneys do more than remove water: they regulate electrolytes and acid–base balance, influence blood pressure, activate vitamin D and produce . Changes in these functions help explain why CKD affects several body systems.
Kidney damage and its wider consequences
 Open diagram larger ↗
Why functioning tissue is lost
Diabetes and hypertension are common causes, while inherited conditions, immune disorders and other diseases can also injure nephrons. Remaining nephrons may initially compensate, which can conceal a developing problem. Over time, maladaptive pressure and scarring may contribute to further loss in some conditions. CKD progression is not identical for everyone and is not inevitable at the same rate. Reduced kidney function also changes how some medicines and their breakdown products are cleared, so drug handling can become an important part of clinical care.
Two useful kinds of evidence
Estimated glomerular filtration rate uses blood markers to approximate filtration, while urine albumin testing looks for abnormal protein leakage. These measures provide different information: filtration may appear relatively preserved while albumin leakage indicates damage. Early CKD often causes few symptoms, so symptoms alone cannot establish its presence or severity. Advanced disease may disturb fluid balance, potassium, acidity, red-cell production and bone-mineral regulation. A single abnormal result may reflect an acute illness or other factors, so duration and clinical context matter. Understanding CKD means tracking persistent changes in several kidney jobs, rather than equating it with the kidneys suddenly making no urine.