More than a storage tube
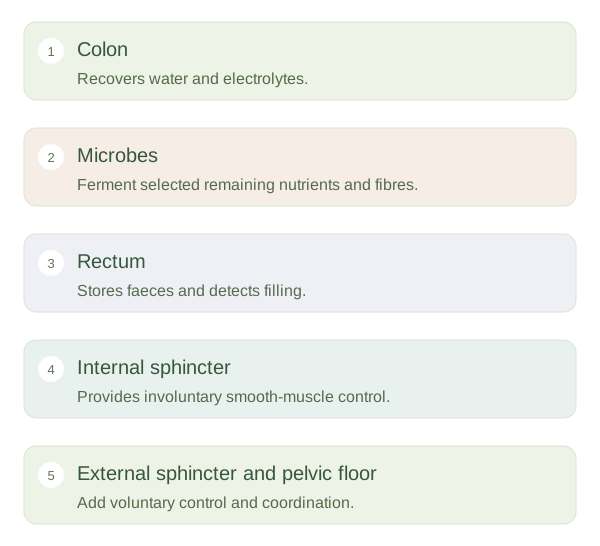
After the small intestine, remaining contents pass into the large intestine. The absorbs water and electrolytes, helping turn liquid contents into more formed faeces. Most digestive absorption has already occurred upstream, but the colon still makes an important contribution to fluid balance. Its lining contains many mucus-producing cells that help protect the surface and ease passage. Movement is slower and differently organised than in the small intestine, allowing time for these functions.
The colon recovers fluid and prepares waste for controlled elimination.
 Open diagram larger ↗
A community with variable effects
The gut includes many microorganisms living in the digestive tract. In the , microbes ferment some carbohydrates that escaped earlier digestion, including certain dietary fibres. Products include short-chain fatty acids that can support colonic cells and influence wider physiology. Microbes also produce gases and participate in processing other substances. The community varies between people and changes with diet, medicines and illness. It should not be described as one universally good set of bacteria or as the explanation for every symptom.
From storage to elimination
The rectum acts as a temporary holding region. Stretch as it fills triggers reflex activity and the sensation of needing to defaecate. The internal anal sphincter is smooth muscle under involuntary control; the external anal sphincter is skeletal muscle with voluntary influence. Pelvic-floor muscles also help maintain and coordinate release. Defaecation therefore involves rectal activity, sphincter relaxation, posture and sometimes abdominal pressure. It is not simply gravity emptying an open tube. Changes in stool frequency or consistency can arise through altered motility, absorption, diet or disease, so no single normal schedule applies to everyone. Understanding the links fluid recovery, microbial metabolism and neural control while keeping these related functions distinct.